
Musculoskeletal Syndrome of the Menopause
An active female patient shared her experience of sudden joint aches and worsening knee pain, which had come on for seemingly no apparent reason. She asked, like many before her, “could it be menopause?”

The cluster of problems women commonly experience in midlife - generalised joint pain, frozen shoulder, greater trochanteric pain syndrome (previously considered as hip bursitis), tennis or golfer’s elbow, carpal tunnel and plantar fasciopathy (previously labelled plantar fasciitis), changes in muscle mass, strength and bone density, worsening osteoarthritis - have been given a name in a recent paper by Dr Vonda Wright and her co authors. The label: “Musculoskeletal Syndrome of the Menopause.” So what does that really mean and what can we do?
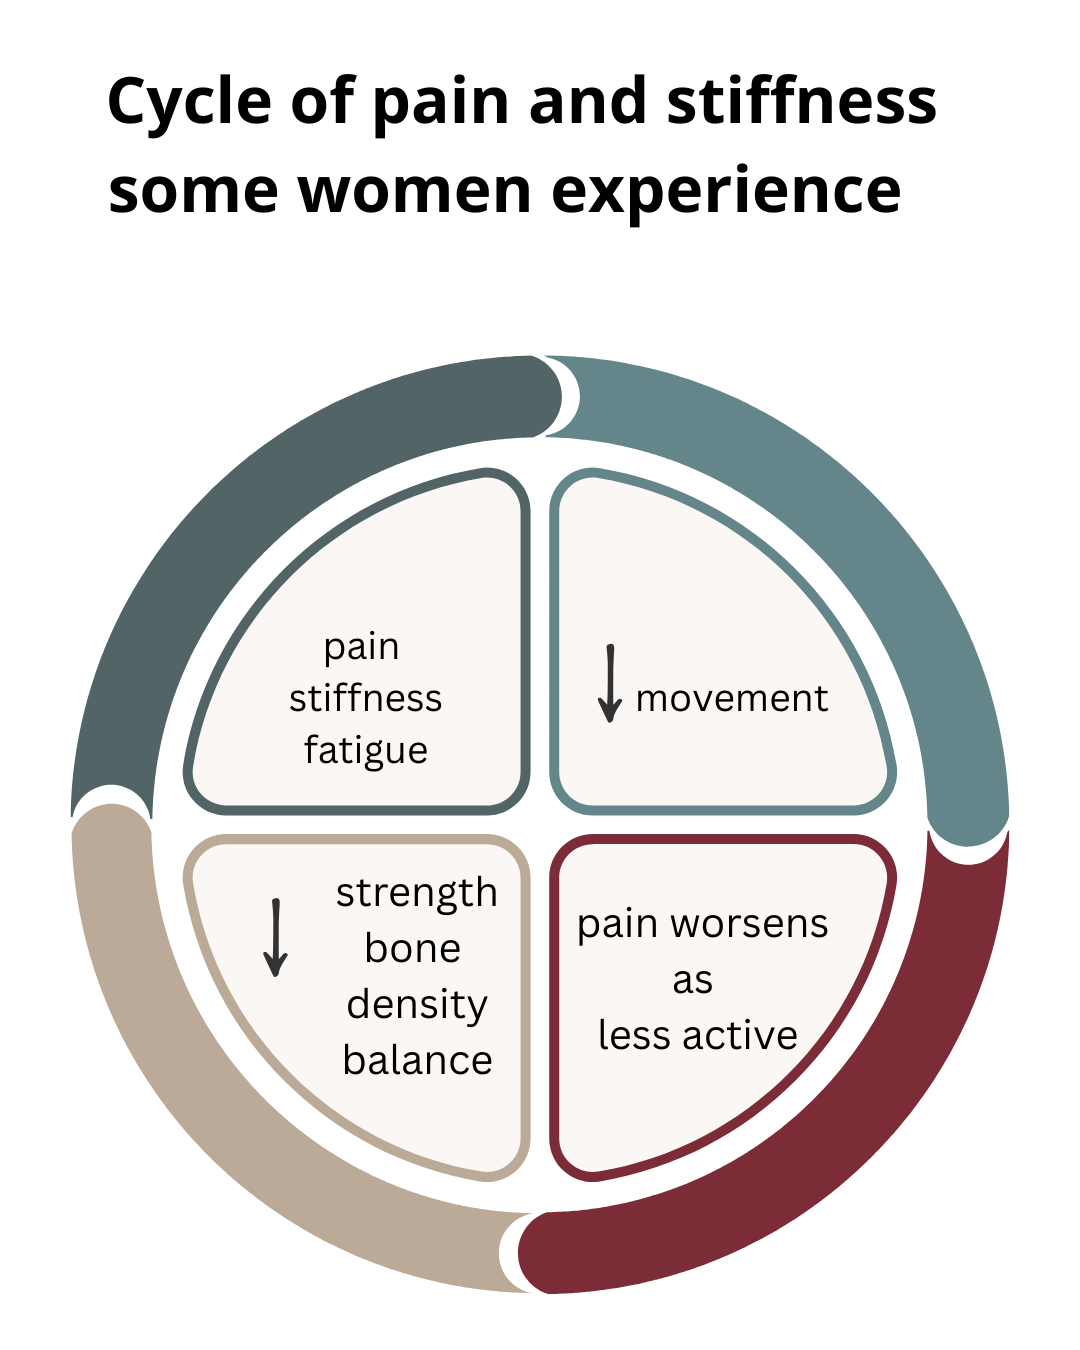
According to this paper, over 70% of all perimenopausal and menopausal women will experience pain, stiffness or problems related to bones, muscle and joints and 25% will experience severe symptoms.
Women can get stuck in a cycle of pain, stiffness and sometimes, exhaustion. This in turn can impact work, family, self esteem and relationships, accompanied by personal and financial costs.
A constellation of processes
Wright’s research group refer to a constellation of processes that occur during perimenopause (when women start experiencing changes in their cycle). The acute drop in oestrodiol, the most biologically active form of oestrogen, impact bones, joints, muscles, tendons, ligaments, nerves, collagen and adipose (body fat). For most, these changes happen between the ages of 45 and 55, and the drop in hormones continues to impact women after this transitional period finishes.

Musculo-skeletal syndrome of the menopause: the effects in real terms.
So is it just the hormones? What else is going on?
When it comes to our bodies, it’s never that simple. We’re products of our history - injuries, surgery and our experiences of pregnancy and childbirth (including caesareans, which cut through our abdominal muscles) shape us. Genetics, general health and lifestyle and the pressure on our joints directly affect us too. While generalised joint pain can be an independent menopausal symptom, research suggests that hormonal changes often compound pre-existing issues and vulnerabilities rather than cause the problem.
For example, if you have a grumbling knee problem, ankle weakness from an old sprain, a stiff lower back and/or hypermobile hips or, like me, overuse your wrist and hands in your job or when gardening, the hormones can have an amplifying effect.
With oestrogen playing a huge role in keeping joints and tendons healthy, it makes sense that a drop in levels may play a part in tipping an old problem into an acute one.
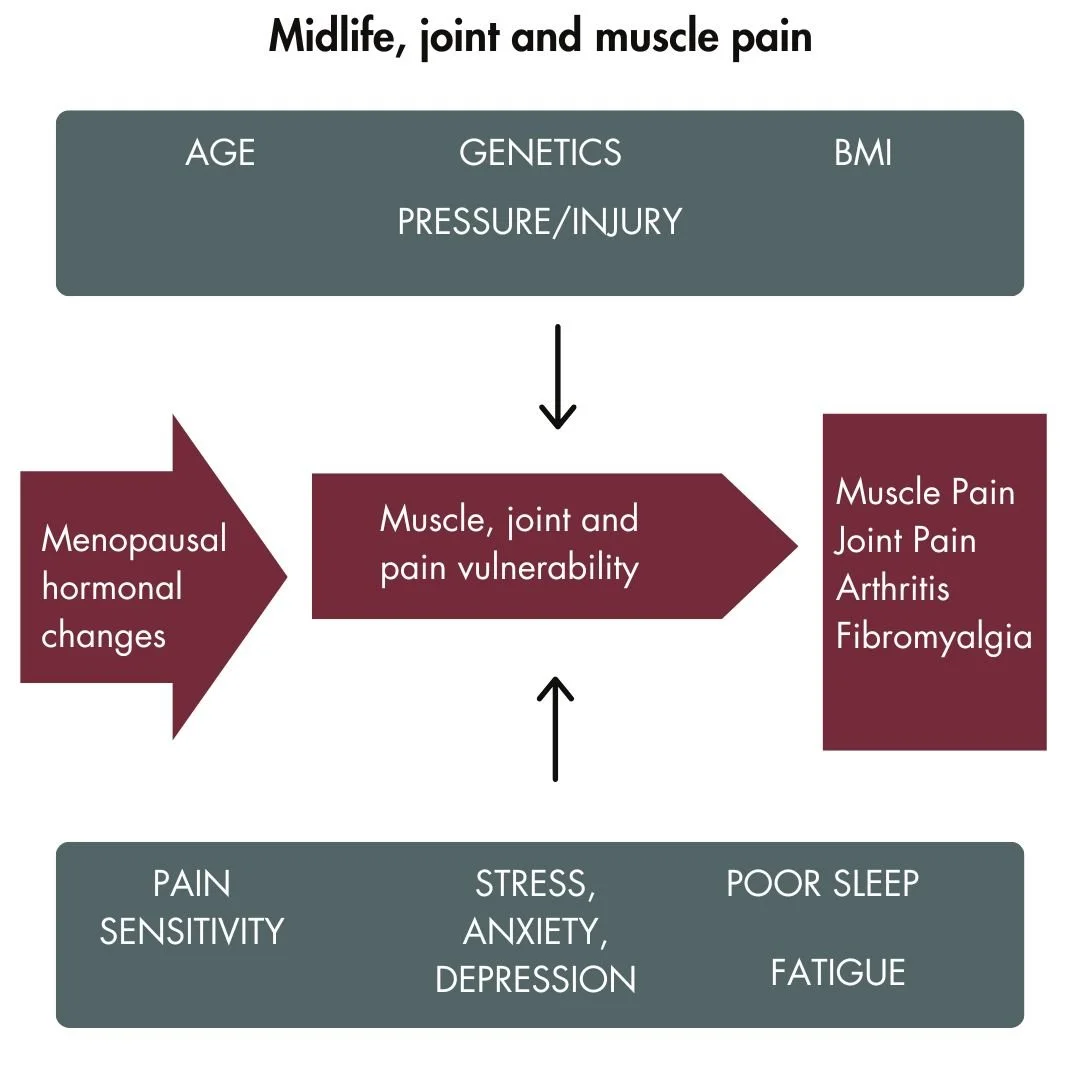
Hormonal changes during menopause are not necessarily causing pain, but can compound the effects of other influences affecting joint and muscle health.
How hormone changes impact specific conditions like gluteal tendinopathy (outer hip pain), plantar fasciopathy, osteoarthritis and frozen shoulder is being explored, with mixed findings in recent studies, and there are many unknowns. What is certain is that moving well and consistent strength, fitness and balance work will help.

A unique opportunity to influence your future
You canticipate the onset of related symptoms and give you the tools to ward off future detrimental processes. Physios can help you understand what aches and pains are associated with menopausal symptoms and what may be caused by other processes or wider health issues. If necessary, we advise women to follow through with medical support wider menopausal symptoms, health conditions and diagnostic scans.

We talk about all these factors and how to help in our membership, The Anchor Collective, which I help run alongside Laura Clark, Menopause Dietitian. Click the button to learn more.
To further unravel the mysteries of perimenopause, pain, collagen and cartilage and for quick wins, click the button here.
References
Dufour, S. et al. Association between lumbopelvic pain and pelvic floor dysfunction in women: A cross sectional study. Musculoskeletal Science and Practice; Volume 34, April 2018: 47-53 https://doi.org/10.1016/j.msksp.2017.12.001
Blumer et al. 2023. Arthralgia of the menopause - a retrospective review. Post Reprod Health. 2023 Jun;29(2):95-97. doi: 10.1177/20533691231172565. Epub 2023 May 1
Bondarev et al. Physical Performance during the menopause transition and the role of physical activity. 2021. J Gerontol A Biol Sci Med Sci Aug 13;76(9):1587-1590. doi: 10.1093/gerona/glaa292
Douglas-Harris, M and Ramaskandhan, J. Menopause and plantar heel pain: a ppi and co production journey. 2024. Newcastle Biomedical Research Centre. https://www.researchgate.net/publication/393281614_Menopause_and_Plantar_Heel_Pain_A_PPI_and_co_production_journey
El Khoudary, S, et al. The menopause transition and women's health at midlife: a progress report from the Study of Women's Health Across the Nation (SWAN). Menopause 2019: 26(10)
Gulati et al. The influence of sex hormones on musculoskeletal pain and osteoarthritis. The Lancet. April 2023. Vol 5 Issue 4.
Isenmann et al. Resistance training alters body composition in middle-aged women depending on menopause - A 20-week control trial BMC Women's Health volume 23, Article number: 526 (2023)
Kang et al. Effect of Sedentary Time on the risk of orthopaedic problems in people aged 50 years and older. The Journal of nutrition, health and aging. 2020. Vol 24 (8) pp 839-845. https://doi.org/10.1007/s12603-020-1391-7
Karlamangla et al. Bone health during the menopause transition and beyond. Obstet Gynecol Clin North Am. 2018 Oct 25;45(4):695–708. doi: 10.1016/j.ogc.2018.07.012
Lu CB, Liu PF, Zhou YS, et al. Musculoskeletal pain during the menopausal transition: a systematic review and meta-analysis. Neural Plast. 2020;2020:8842110–8842110. doi: 10.1155/2020/8842110
Chan S, Gomes A, Singh RS. Is menopause still evolving? Evidence from a longitudinal study of multiethnic populations and its relevance to women’s health. BMC Womens Health. 2020;20(1):74. doi: 10.1186/s12905-020-00932-8.
Rothschild C and Collingwood T. Maximising Running Participation through menopause. Journal of Women's & Pelvic Health Physical Therapy 47(2):p 133-143, April/June 2023. | DOI: 10.1097/JWH.0000000000000276
Saltzman et al. Poster 188: Is Hormone Replacing Therapy Associated with Reduced Risk of Adhesive Capsulitis in Menopausal Women? A Single Center Analysis. Orthop J Sports Med. 2023 Jul 31;11(7 suppl3):2325967123S00174. doi: 10.1177/2325967123S00174
Volpi et al. Muscle tissue changes with aging. Curr Opin Clin Nutr Metab Care. 2004 Jul;7(4):405–410. 10.1097/01.mco.0000134362.76653.b2
Wang et al. Mechanistic insights into the anti-fibrotic effects of Estrogen via the PI3K-Akt Pathway in Frozen Shoulder. The Journal of Steroid Biochemistry and Molecular Biology, 2025 p.106701. doi: 10.1016/j.jsbmb.2025.106701.
Wright et al. Musculo-skeletal Syndrome of the Menopause. Climacteric Oct 2024.27(5):466-472. doi: 10.1080/13697137.2024.2380363.
Williams et al. Hormone replacement therapy (conjugated oestrogens plus bazedoxifene) for post-menopausal women with symptomatic hand osteoarthritis: primary report from the HOPE-e randomised, placebo-controlled, feasibility study. Lancet Rheumatol. 2022 Sep 21;4(10):e725-e737. doi: 10.1016/S2665-9913(22)00218-1
